


Example · sample answers
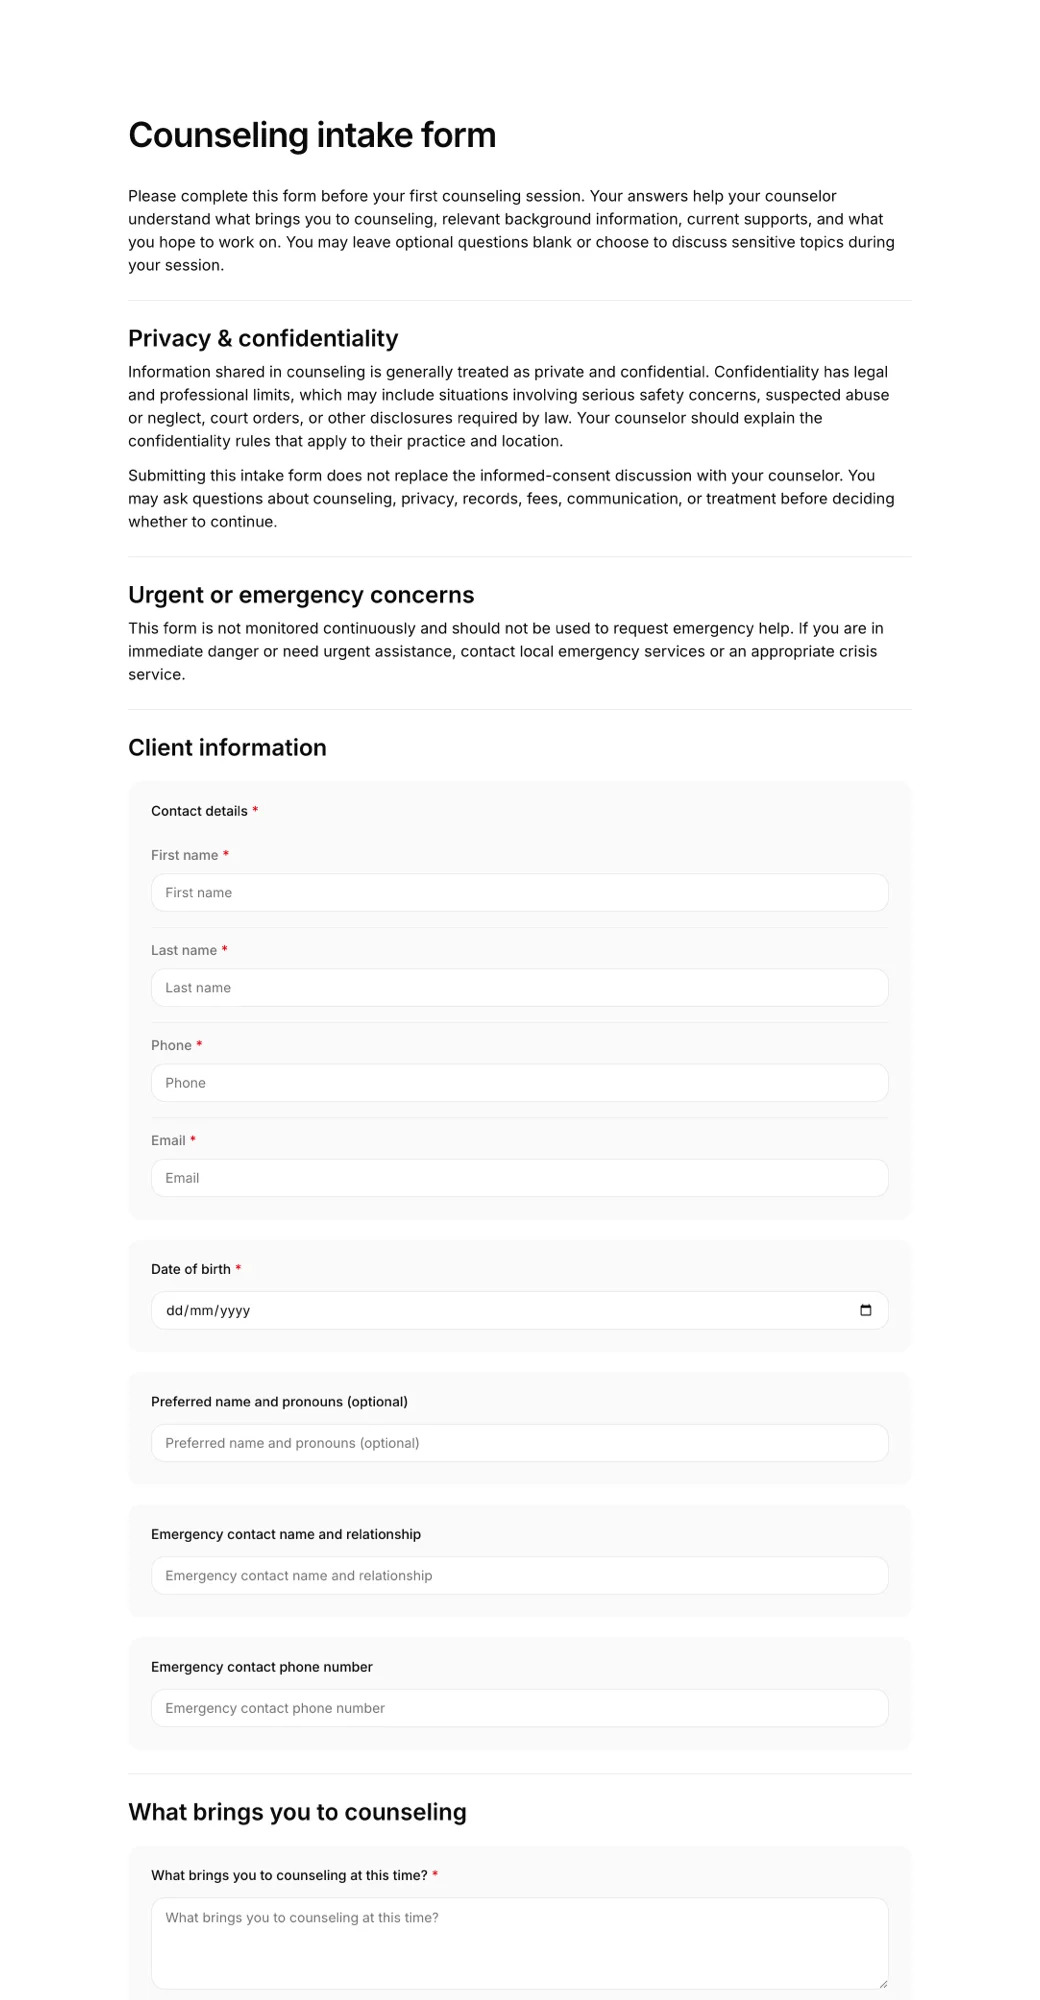
Counseling intake form
Please complete this form before your first counseling session. Your answers help your counselor understand what brings you to counseling, relevant background information, current supports, and what you hope to work on. You may leave optional questions blank or choose to discuss sensitive topics during your session.
Privacy & confidentiality
Information shared in counseling is generally treated as private and confidential. Confidentiality has legal and professional limits, which may include situations involving serious safety concerns, suspected abuse or neglect, court orders, or other disclosures required by law. Your counselor should explain the confidentiality rules that apply to their practice and location.
Submitting this intake form does not replace the informed-consent discussion with your counselor. You may ask questions about counseling, privacy, records, fees, communication, or treatment before deciding whether to continue.
Urgent or emergency concerns
This form is not monitored continuously and should not be used to request emergency help. If you are in immediate danger or need urgent assistance, contact local emergency services or an appropriate crisis service.
Client information
Contact details
- First name
- Jordan
- Last name
- Smith
- Phone
- (555) 014-2298
- jordan.smith@example.com
Date of birth
April 12, 1990
Preferred name and pronouns (optional)
Jordan
Emergency contact name and relationship
Morgan Smith, sister
Emergency contact phone number
(555) 201-4477
What brings you to counseling
What brings you to counseling at this time?
Which concerns would you like support with? Select all that apply.
- Anxiety, worry, or panic
- Low mood or depression
- Stress or burnout
- Relationship or family concerns
- Grief or loss
- Trauma or difficult experiences
- Self-esteem or confidence
- Anger or emotional regulation
- Life transitions or major changes
- Work or school concerns
- Sleep difficulties
- Attention or concentration
- Eating or body-image concerns
- Alcohol or substance use
- Parenting
- Identity, sexuality, or cultural concerns
- Personal growth or self-understanding
- Other
How long have your main concerns been affecting you?
- Less than 1 month
- 1–6 months
- 6–12 months
- More than 1 year
- They come and go
- Unsure
How much are these concerns affecting your daily life right now?
- A little
- Moderately
- Significantly
- Very significantly
- Unsure
What would you most like to get from counseling?
Counseling & health history
Have you received counseling, psychotherapy, or other mental health treatment before?
- No
- Yes, in the past
- Yes, currently
If yes, what was helpful or unhelpful about your previous treatment?
None.
List any previous mental health diagnoses, psychiatric hospitalizations, or other significant mental health history you would like your counselor to know about.
None.
List any current medications that may be relevant to your care, including psychiatric medications.
None.
Are you currently receiving care from another mental health or healthcare professional? If yes, please provide any details you think are relevant.
Are there traumatic or very difficult experiences in your history that may be relevant to counseling?
- No
- Yes
- Unsure
- I prefer to discuss this in session
Are there physical health conditions, chronic pain, recent medical changes, sleep concerns, or other health factors that may be relevant to counseling?
None.
Is there anything about alcohol, cannabis, prescription medication use, or other substance use that you would like your counselor to know?
None.
Relationships, daily life & support
Who are the important people or sources of support in your life?
Tell us anything relevant about your current work, school, caregiving, or living situation.
Are there cultural, spiritual, identity, family, accessibility, or community factors you would like your counselor to understand or consider?
None.
Safety
The following questions help identify concerns that may need prompt discussion. They are not a substitute for a clinical risk assessment.
Have you had thoughts of suicide or of not wanting to be alive?
- No
- Yes, in the past but not recently
- Yes, recently but not currently
- Yes, currently
- I prefer to discuss this with my counselor
Have you intentionally harmed yourself?
- No
- Yes, in the past
- Yes, recently
- I prefer to discuss this with my counselor
Have you had thoughts of seriously harming someone else?
- No
- Yes, in the past but not recently
- Yes, recently but not currently
- Yes, currently
- I prefer to discuss this with my counselor
Do you currently feel safe where you live and in your close relationships?
- Yes
- No
- Unsure
- I prefer to discuss this with my counselor
If you would like, provide any additional information about current safety concerns, past self-harm, suicide attempts, violence, or situations your counselor should know about.
None.
Counseling preferences
What would help you feel comfortable, respected, and supported during counseling?
Do you need any accessibility, communication, language, sensory, mobility, or other accommodations?
None.
Acknowledgment & signature
I confirm that the information I provided is accurate to the best of my knowledge and I will let my counselor know about important changes that may affect my care.
I understand that this form is not monitored continuously and is not a way to request emergency or crisis assistance.
I understand that counseling information is generally confidential but that confidentiality has limits required by applicable law and professional obligations, which my counselor will explain.
I understand that counseling is a collaborative process, that I may ask questions or discuss concerns about treatment, and that specific results cannot be guaranteed.
I understand that completing this form does not replace the counselor's full informed-consent process or any privacy, financial, telehealth, or practice policies that may separately apply.
Client signature




